Die Darmbewohner produzieren eine Substanz, die Gefe belasten und die Wahrscheinlichkeit fr Herzprobleme erhhen kann

[4] [5] Appropriate clinical management for patients with comorbid metabolic conditions and problematic alcohol use should include: Comprehensive assessment of alcohol consumption patterns using validated screening tools (AUDIT, AUDIT-C) Referral to addiction medicine specialists or behavioral health providers for evidence-based AUD treatment, especially with red flags such as history of severe withdrawal, seizures, delirium tremens, pregnancy, severe liver disease, or suicidality Consideration of FDA-approved pharmacotherapies for alcohol use disorder (naltrexone, acamprosate, disulfiram) with attention to their specific contraindications [9] [11] If GLP-1 therapy is indicated for diabetes or obesity, close monitoring for changes in alcohol consumption and related behaviors Patient education emphasizing that any effects on alcohol cravings are not established therapeutic benefits Regular follow-up to assess medication adherence, adverse effects, and overall treatment response Patients should never discontinue evidence-based treatments for alcohol use disorder in favor of unproven approaches

They can help you make changes safely and manage any symptoms as semaglutide leaves your body
If youre new to exercise, consult with your provider at InsideOut Aesthetics & Wellness before starting any new activity
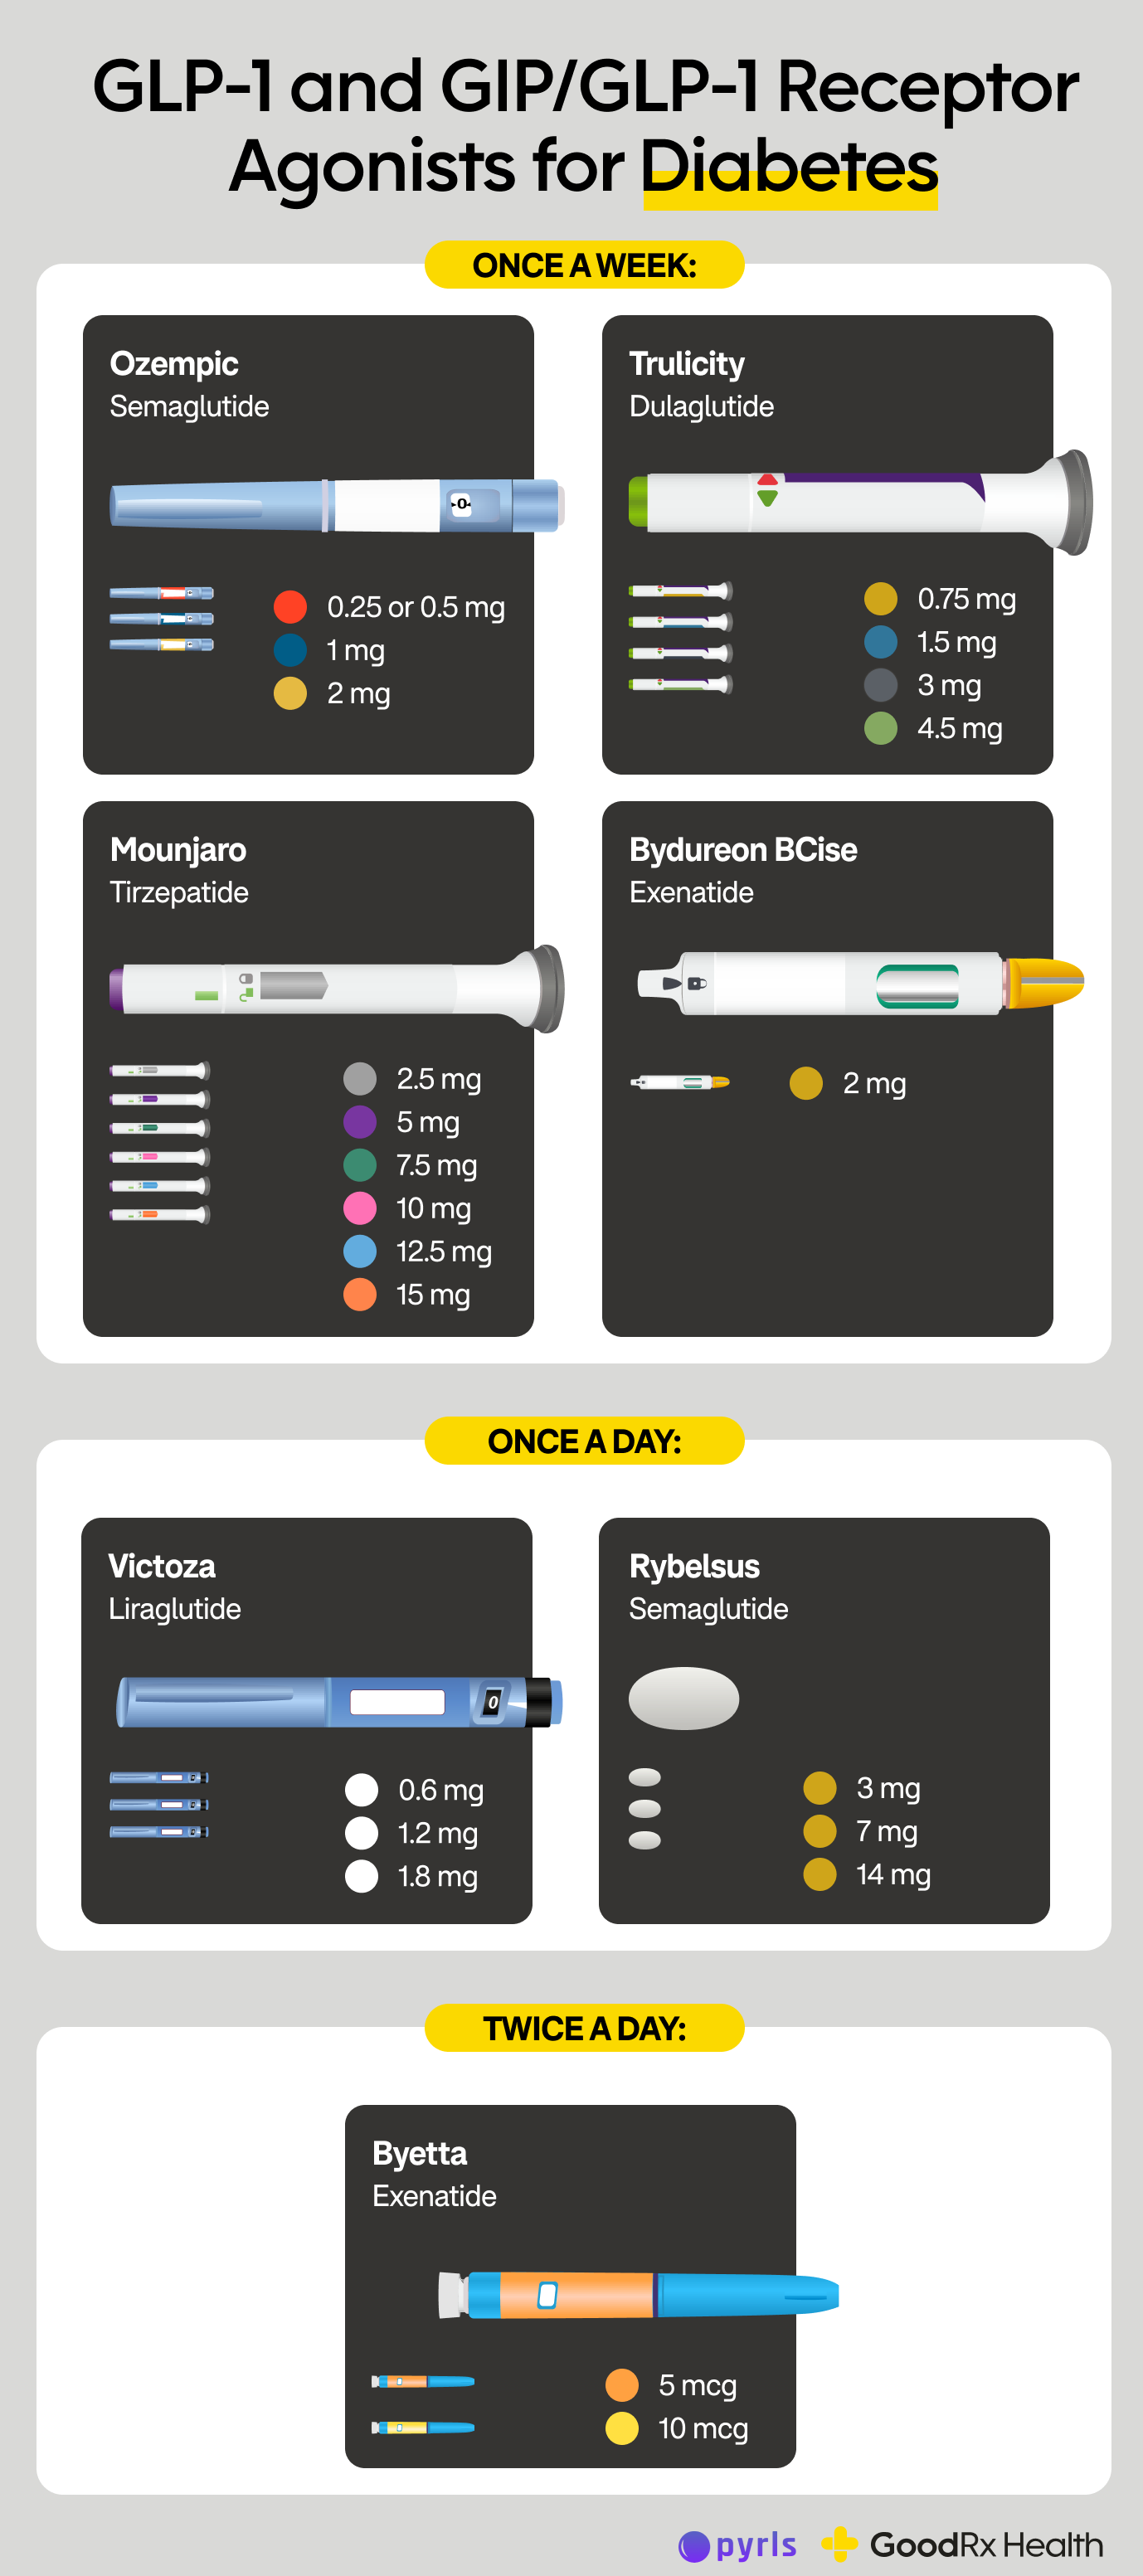
Dose adjustments between standard increments The FDA titration schedule jumps from 0.25 to 0.5 to 1.0 mg